

The race is on to find a vaccine against the new COVID-19 coronavirus. Professor Jonathan Heeney explains why a cautious approach is needed and how his team is using new technology developed for influenza and Ebola viruses to target the new infection.
It is hard now to conceive that two months ago, few people had heard of the new coronavirus. Now, the virus, which causes the disease COVID-19, has spread to every corner of the globe. The World Health Organization has officially declared the outbreak a pandemic.
With the threat of hundreds of thousands – possibly millions – of people being infected and healthcare systems becoming overwhelmed, the race is on to develop a vaccine that will protect individuals and slow the spread of the disease. But Professor Jonathan Heeney, Head of the Laboratory of Viral Zoonotics at the University of Cambridge, and one of the people working on a vaccine, says that coronaviruses present a particular challenge to vaccine developers.
Coronaviruses are named after their appearance: they are spherical objects, on the surface of which sit ‘spike’ proteins. The virus uses these spikes to attach to and invade cells in our body. Once inside, the virus uses the cell’s own machinery to help itself replicate and spread throughout the body, causing disease and allowing it to transmit onwards.
Traditionally, scientists would develop vaccines that programme the body to produce antibodies that recognise and block these spikes. But this strategy can misfire with coronaviruses due to a phenomenon known as ‘antibody-induced enhancement’ or ‘vaccine-induced enhancement’, says Heeney.
“If you make antibodies against the spike, they can end up binding to it and helping the virus invade important immune cells known as monocyte-macrophages. Rather than destroying the virus, these cells can then end up being reprogrammed by the viruses, exacerbating the immune response and making the disease much, much worse than it would otherwise be.”





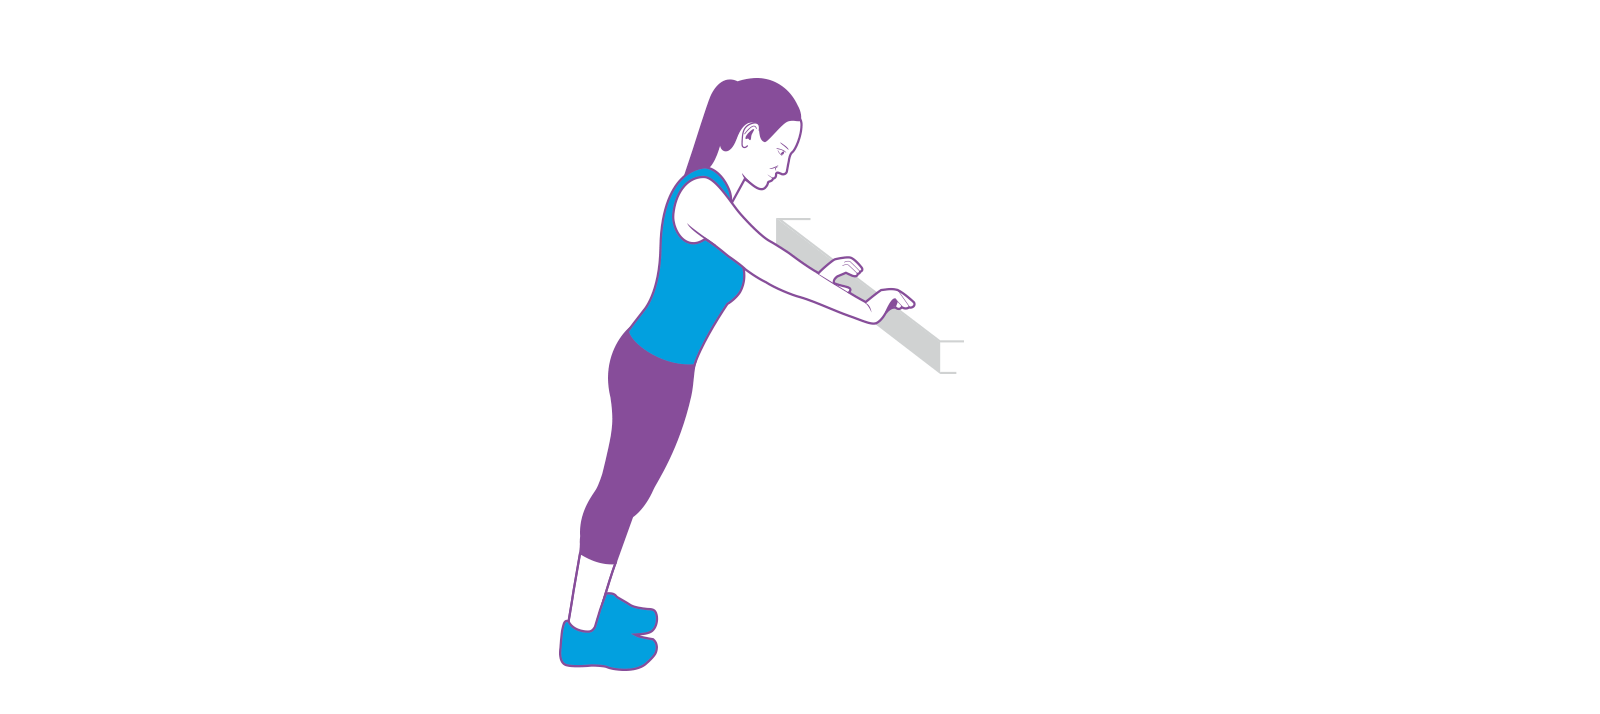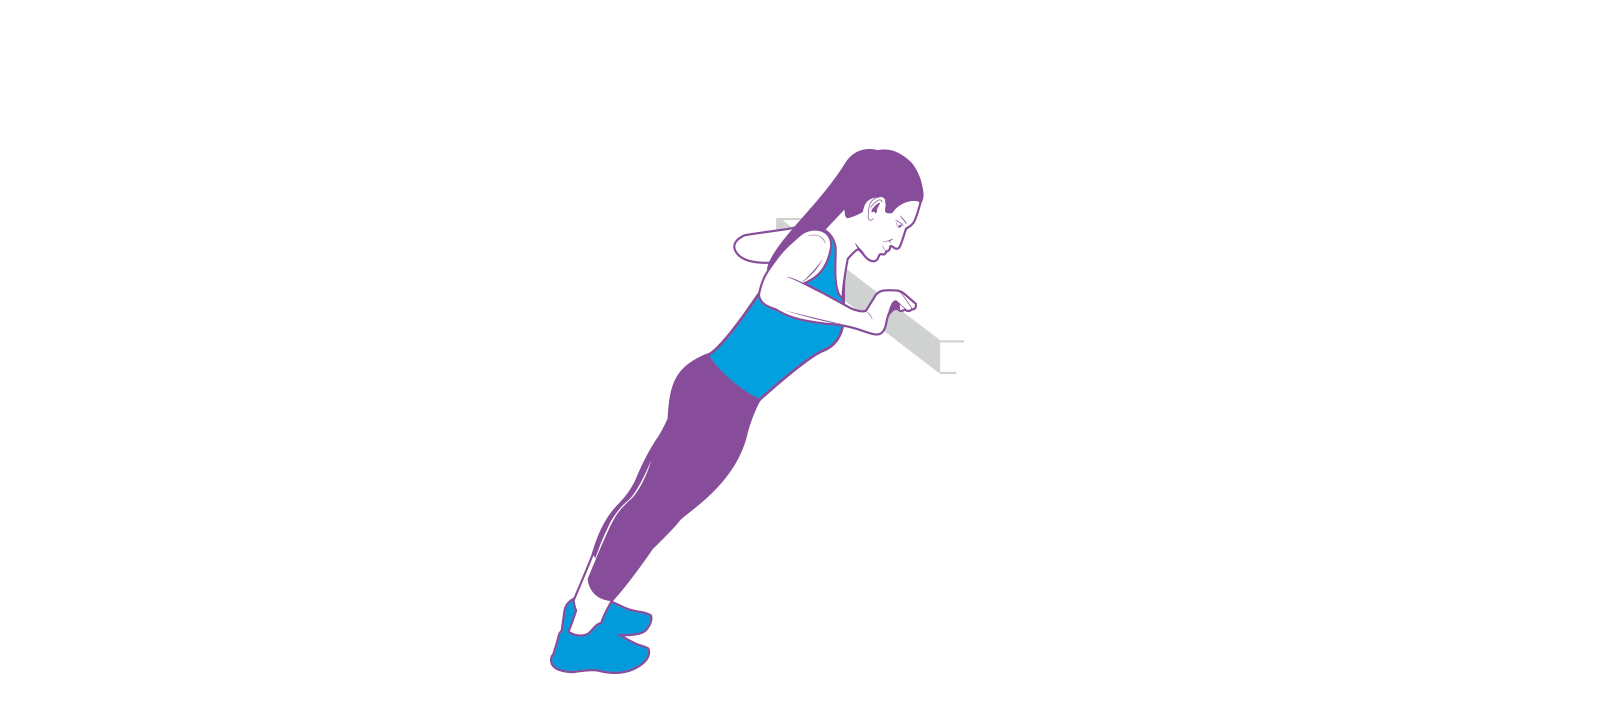 Place your hands on the edge of a counter, just beyond shoulder-width apart. Lower into a push-up then press back up. Repeat 10 to 12 times. For more of a challenge, walk your feet farther away from the counter.

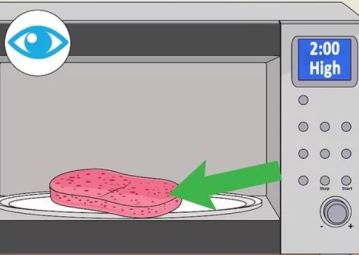 Microwaves are used in medicine for disinfection of soft contact lenses, dental instruments, dentures, milk, and urinary catheters for intermittent self-catheterization925-931. However, microwaves must only be used with products that are compatible (e.g., do not melt) 931. Microwaves are radio-frequency waves, which are usually used at a frequency of 2450 MHz. The microwaves produce friction of water molecules in an alternating electrical field. The intermolecular friction derived from the vibrations generates heat and some authors believe that the effect of microwaves depends on the heat produced while others postulate a nonthermal lethal effect932-934. The initial reports showed microwaves to be an effective microbicide. The microwaves produced by a “home-type” microwave oven (2.45 GHz) completely inactivate bacterial cultures, mycobacteria, viruses, and G. stearothermophilus spores within 60 seconds to 5 minutes depending on the challenge organism933, 935-937. Another study confirmed these resuIts but also found that higher power microwaves in the presence of water may be needed for sterilization932. Complete destruction of Mycobacterium bovis was obtained with 4 minutes of microwave exposure (600W, 2450 MHz)937. The effectiveness of microwave ovens for different sterilization and disinfection purposes should be tested and demonstrated as test conditions affect the results (e.g., presence of water, microwave power). Sterilization of metal instruments can be accomplished but requires certain precautions.926. Of concern is that home-type microwave ovens may not have even distribution of microwave energy over the entire dry device (there may be hot and cold spots on solid medical devices); hence there may be areas that are not sterilized or disinfected. The use of microwave ovens to disinfect intermittent-use catheters also has been suggested. Researchers found that test bacteria (e.g., E. coli, Klebsiella pneumoniae, Candida albicans) were eliminated from red rubber catheters within 5 minutes 931. Microwaves used for sterilization of medical devices have not been FDA cleared.

 “The finding in two randomised trials that advice to use ibuprofen results in more severe illness or complications helps confirm that the association seen in observational studies is indeed likely to be causal. Advice to use paracetamol (acetaminophen) is also less likely to result in complications.”
 Ian Jones, a professor of virology at the University of Reading, said that ibuprofen’s anti-inflammatory properties could “dampen down” the immune system, which could slow the recovery process. He added that it was likely, based on similarities between the new virus (SARS-CoV-2) and SARS I, that covid-19 reduces a key enzyme that part regulates the water and salt concentration in the blood and could contribute to the pneumonia seen in extreme cases. “Ibuprofen aggravates this, while paracetamol does not,” he said.

 Nathan Pritikin was a college dropout who became an entrepreneur. While doing research for the government during World War II, he observed that populations that had extremely limited food availability because of the war had substantially reduced mortality from cardiovascular disease—something unexpected at a time when cardiovascular disease was thought to be due to stress.

 In this Podcast Extra, we hear from epidemiologists, genomicists and social scientists about how they’re working to tackle the coronavirus and what they’ve learned so far.
 Intellicurious
